
You’ve spent years working around a tongue that never quite moves the way it should, clearing your speech in certain words, avoiding certain foods, or waking up with jaw tension you can’t explain. You may not have connected any of it to the thin strip of tissue under your tongue. Tongue-tie, known clinically as ankyloglossia, is usually framed as a newborn feeding issue, but a restricted lingual frenulum can persist unnoticed for decades.
Tongue-tie in adults is a real and treatable condition, most often identified through a functional evaluation with a speech-language pathologist, myofunctional therapist, or dentist trained in frenulum assessment, rather than by appearance alone. Many adults with a restricted frenulum adapted so early in life that the workaround feels normal: compensations in speech, chewing, or swallowing that mask the original cause.
The gap between how common this condition is and how rarely it gets diagnosed in adulthood is significant. Recognizing the signs, and mentioning them at your next visit with a dental team like Florida Dental Implant Center, can be the difference between years of unexplained discomfort and a straightforward fix.
Could a Tongue-Tie Be Causing Your Speech or Eating Problems?
A tongue-tie limits how far and how precisely your tongue can move, and that restriction can quietly shape how you talk, chew, and swallow well into adulthood. Because the effects build gradually, most adults attribute the symptoms to something else entirely.
What Adult Ankyloglossia Is and Why It Can Go Unnoticed
Ankyloglossia happens when the lingual frenulum, the band of tissue connecting the tongue to the floor of the mouth, is tighter or shorter than it should be. In infants, this gets caught during feeding evaluations. In adults, no one is checking, so it slides by.
Many people with tongue-tie develop compensatory movement patterns early in childhood. Those patterns become automatic, so the restriction itself never registers as a problem. It just feels like “how you’ve always talked” or “how you’ve always eaten.”
Signs of Restricted Tongue Mobility You Can Recognize
A few physical signs point toward tongue-tie. You may notice:
- Difficulty lifting your tongue tip to your upper front teeth or the roof of your mouth
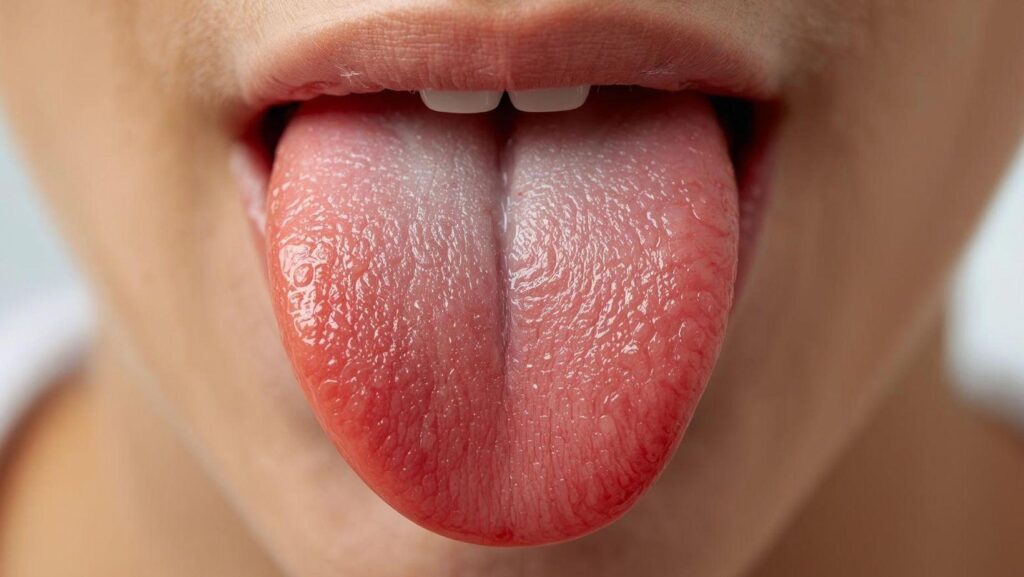
- A heart-shaped or notched appearance when you stick your tongue out
- Trouble sticking your tongue out past your lower lip
- Jaw or neck tension that shows up after talking or eating for extended periods
- A visible thick or tight band of tissue under the tongue
None of these alone confirms tongue-tie, but a cluster of them is worth a professional look.
How Tongue Restriction Can Affect Speech, Chewing, and Swallowing
Limited tongue mobility can affect sounds that require the tongue tip to reach the roof of the mouth, including T, D, L, N, and S. Speech may sound effortful or slightly unclear even after years of speech habits.
Eating presents its own patterns. Chewing may take longer, food may pocket in the cheeks, and swallowing can feel like extra work compared to people without restriction. Some adults also notice their tongue tires during long conversations or meals.
Getting an Accurate Adult Tongue-Tie Assessment
An accurate diagnosis depends on how the tongue functions, not just how the frenulum looks. Clinicians trained in this area use structured evaluation tools and functional testing to separate true restriction from other causes of similar symptoms.
What Clinicians Look for Beyond the Frenulum’s Appearance
A visual check is a starting point, not the full picture. Providers assess range of motion: how far the tongue elevates, how it moves side to side, and whether the tip can reach the alveolar ridge without excessive strain.
Some clinicians apply validated tools such as the Kotlow classification or the Hazelbaker Assessment Tool for Lingual Frenulum Function (HATLFF) to score mobility and function objectively rather than relying on a subjective glance. Function during speech and swallowing tasks matters as much as the resting appearance of the tissue.
Which Professionals Can Evaluate Tongue Function
Several types of providers can assess adult tongue-tie, and they often work together. A speech-language pathologist evaluates articulation and oral motor function. A myofunctional therapist assesses tongue posture, swallowing patterns, and muscle coordination. Dentists and oral surgeons trained in frenectomy procedures evaluate the tissue itself and determine whether a surgical release is appropriate.
Starting with a speech-language pathologist or myofunctional therapist gives you a functional baseline before any surgical conversation begins.
When Symptoms May Have Another Cause
Not every speech or swallowing difficulty traces back to the tongue. TMJ disorders, sleep-disordered breathing, allergies affecting nasal breathing, and general articulation disorders unrelated to tongue mobility can produce overlapping symptoms.
A thorough evaluation rules these out or identifies them as contributing factors alongside tongue restriction, rather than assuming tongue-tie explains everything.
When Treatment Is Appropriate and What to Expect
Treatment for adult tongue-tie ranges from targeted therapy alone to a minor surgical release paired with structured follow-up. The right path depends on symptom severity, how much the restriction limits daily function, and how you respond to conservative approaches first.
When Observation or Therapy May Be Enough
Not every adult with a tightened frenulum needs surgery. If symptoms are mild, myofunctional therapy or speech therapy alone can improve tongue coordination and reduce compensatory strain.
Clinicians often use response to this conservative therapy as a diagnostic clue: meaningful improvement suggests the tissue restriction isn’t the primary limiting factor, while a therapy plateau despite consistent effort points toward a structural release as the next step.
Adult Frenectomy Options and Recovery
A frenectomy releases the tight tissue band, typically using laser or scalpel techniques performed under local anesthesia. The procedure itself is brief, often under thirty minutes.
Recovery involves mild soreness for several days, with most adults returning to normal diet and speech within a week or two. Post-procedure stretching exercises are usually prescribed early to prevent the tissue from reattaching or scarring as it heals.
Why Follow-Up Exercises and Therapy May Matter
Surgery releases the tissue restriction, but it doesn’t automatically retrain the muscle patterns built up over years. Myofunctional therapy after a frenectomy helps the tongue learn new resting posture, swallowing mechanics, and articulation patterns now that the physical limitation is gone.
Skipping this step is one of the more common reasons adults feel disappointed with results despite a technically successful release.
Finding Relief Starts With a Functional Evaluation
Adult tongue-tie is treatable once it’s correctly identified, and identification starts with looking at how the tongue functions rather than how it appears at a glance. If you recognize the speech patterns, eating habits, or jaw tension described here, a functional evaluation from a speech-language pathologist, myofunctional therapist, or dentist experienced in frenulum assessment is the practical next step. Whether that leads to targeted therapy, a frenectomy, or a combination of both depends on your specific symptoms and how your tongue responds to initial treatment.

